Why Your Breech Position Baby Might Be the Safest Choice You Haven’t Considered
Table of Contents
- The Complete Overview of Breech Position Babies
- Historical Background and Evolution
- Core Mechanisms: How It Works
- Key Benefits and Crucial Impact
- Major Advantages
- Comparative Analysis
- Future Trends and Innovations
- Conclusion
- Comprehensive FAQs
- Q: Is a vaginal breech birth safe for my baby?
- Q: Can external cephalic version (ECV) turn a breech baby head-down?
- Q: What are the signs that a vaginal breech birth may not be safe?
- Q: How can I find a provider experienced in breech births?
- Q: Are there specific exercises or positions to encourage a breech baby to turn?
- Q: What’s the recovery like after a vaginal breech birth?
- Q: Can a breech baby be delivered safely at home?
- Q: Does insurance cover breech birth planning or ECV?
- Q: What’s the success rate of vaginal breech births?
The idea of a breech position baby—where the baby’s feet or buttocks present first instead of the head—has long been shrouded in medical caution. For decades, obstetric guidelines have steered parents toward cesarean sections (C-sections) when a baby remains breech at term, framing it as a high-risk scenario. Yet beneath the surface of this clinical directive lies a more nuanced story: one of evolving research, cultural shifts in birth practices, and the quiet resilience of women who’ve successfully delivered breech babies vaginally. The reality is far more complex than the binary "C-section or not" narrative suggests.
What if the conversation around breech position babies isn’t just about risk mitigation but about informed choice? Modern obstetrics now acknowledges that not all breech births are equal—some babies are simply better positioned for a vaginal delivery than others. The key lies in understanding the mechanics of the breech presentation, the role of maternal pelvis anatomy, and the critical distinction between "frank breech" (legs folded up) and "complete breech" (legs crossed), which can dramatically alter outcomes. This isn’t just academic; it’s about empowering parents to ask the right questions before their due date.
The stigma around breech position babies persists, in part, because the medical community has historically prioritized predictability over flexibility. But as birth practices evolve—with growing interest in midwifery-led care and evidence-based alternatives—the dialogue is changing. The question is no longer if a breech birth is possible, but how to optimize the conditions for a safe delivery, whether that means external cephalic version (ECV), a planned home birth, or a hospital setting with a skilled breech-trained provider. The goal? To shift from fear to foresight.

The Complete Overview of Breech Position Babies
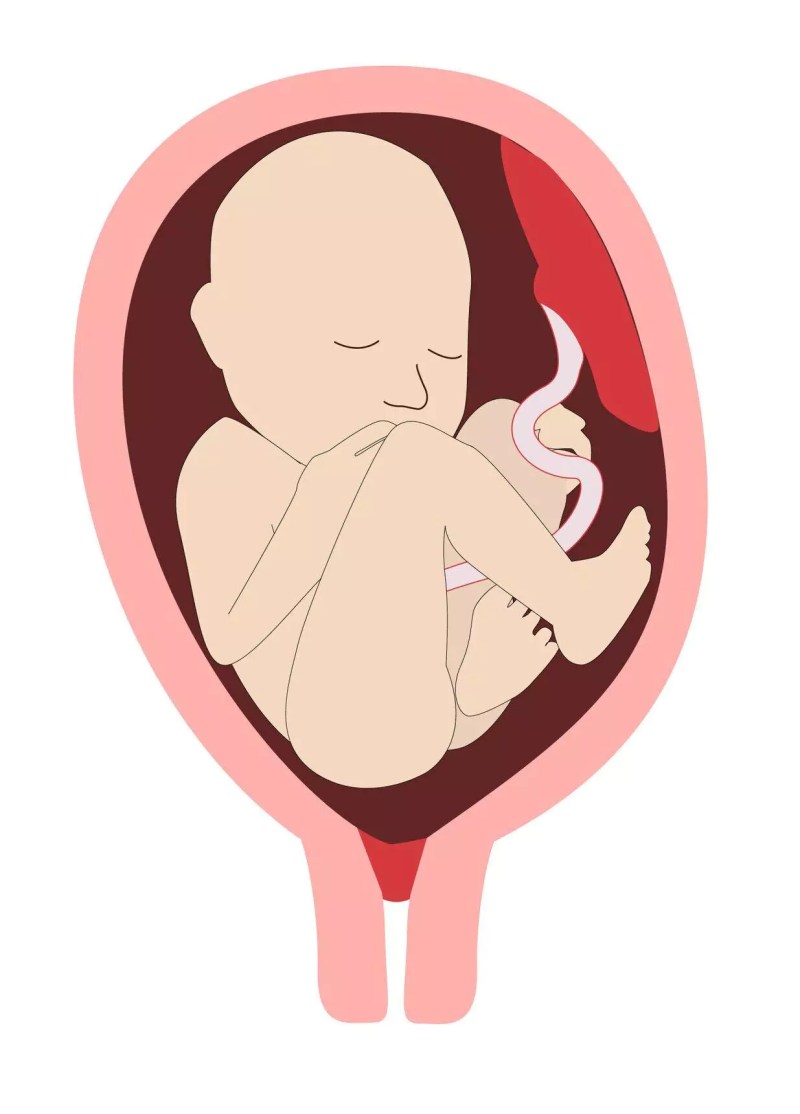
The term "breech position baby" refers to any fetal presentation where the buttocks, feet, or knees emerge first during labor, rather than the head. While head-down (cephalic) presentations account for over 96% of births, breech births occur in roughly 3–4% of full-term pregnancies. The variation in breech types—frank, complete, footling (single or double), and transverse—each carries distinct implications for delivery. Frank breech, where the baby’s legs are folded up against the torso, is the most common and often considered the most favorable for a vaginal birth, provided the pelvis is adequately sized and the baby’s weight is within a manageable range.What’s often overlooked is that the decision to pursue a vaginal breech birth isn’t just about the baby’s position but also about the mother’s anatomy, the provider’s expertise, and the availability of emergency cesarean support. Historically, breech deliveries were managed routinely by midwives and physicians, but the rise of C-sections in the mid-20th century—driven by concerns over hypoxia and trauma—led to their decline. Today, the conversation is reopening, with some countries (like the Netherlands and Australia) reporting higher rates of successful vaginal breech births under specific conditions. The crux lies in balancing evidence-based medicine with individualized care.
Historical Background and Evolution
The management of breech position babies has undergone radical shifts over centuries, reflecting broader changes in obstetric philosophy. In ancient civilizations, breech births were often met with fatalism or ritualistic interventions, but by the 18th century, European physicians like William Smellie began documenting techniques for assisted vaginal breech deliveries. Smellie’s innovations—such as the use of forceps and the "breech extraction" method—reduced maternal mortality, though the risks to the baby remained high. By the 19th century, the advent of antiseptic surgery and anesthesia further tilted the balance toward C-sections, which were perceived as safer for both mother and child.The 20th century cemented the C-section as the default for breech births, largely due to the 1959 publication of the "Term Breech Trial," which suggested higher neonatal mortality rates in vaginal breech deliveries. However, this study was later criticized for methodological flaws, and subsequent research—such as the 2000 Term Breech Trial—revealed that planned home births with experienced midwives yielded comparable outcomes to hospital C-sections in low-risk cases. This resurgence of interest in vaginal breech births highlights a critical tension: while medicine seeks standardization, birth is inherently unpredictable. The challenge is to reconcile safety with autonomy.
Core Mechanisms: How It Works
The mechanics of delivering a breech position baby hinge on the baby’s orientation, the mother’s pelvic dimensions, and the provider’s ability to guide the descent. In a frank breech presentation, the baby’s head—typically the largest diameter—remains flexed and follows the body through the birth canal, which can ease delivery if the pelvis is sufficiently wide. The provider must monitor for signs of head entrapment (where the head fails to deliver after the body) or cord prolapse, both of which may necessitate an emergency C-section. Techniques like the "Lotus Birth" position (mother squatting) or manual rotation of the baby’s head can facilitate delivery, but these require advanced training.What distinguishes a successful vaginal breech birth from a high-risk scenario is often the provider’s experience. Studies show that obstetricians with high volumes of breech deliveries are more likely to achieve favorable outcomes. This expertise extends to recognizing when a breech baby is "ideal" for vaginal birth—typically under 3,800 grams (8.4 lbs), with no signs of prematurity or malpresentation. The process also demands real-time adaptability; if labor stalls or the baby shows distress, the provider must swiftly transition to a C-section. The goal isn’t to eliminate risk but to mitigate it through preparation and skilled intervention.
Key Benefits and Crucial Impact
The decision to pursue a vaginal delivery for a breech position baby is not merely about avoiding surgery; it’s about reclaiming agency in childbirth. For mothers who opt for this route, the benefits extend beyond physical recovery. Vaginal breech births are associated with shorter hospital stays, reduced risk of infection (compared to C-sections), and a lower likelihood of blood transfusions or thromboembolic events. Psychologically, the experience can be empowering, particularly for women who prioritize a physiological birth. That said, the impact is deeply personal: some mothers feel relief in the predictability of a scheduled C-section, while others view vaginal breech birth as a testament to their body’s resilience.The medical community’s growing acceptance of vaginal breech births also reflects a broader shift toward patient-centered care. No longer is the default assumption that a breech baby equals a C-section. Instead, providers are encouraged to discuss the options—including external cephalic version (ECV), which can turn a breech baby head-down by the 37th week—and tailor recommendations to the individual. This evolution underscores a fundamental truth: birth is not a one-size-fits-all process. The key is to ensure that women have access to accurate information and providers who can navigate the complexities of a breech presentation without resorting to blanket restrictions.
"Breech birth is not a medical emergency; it’s a variation of the normal process of birth. The question isn’t whether it’s safe, but how we can make it safer for those who choose it."
— Dr. Marshall Klaus, pediatrician and advocate for physiological childbirth
Major Advantages
- Reduced surgical risks: Avoids the complications of C-sections, including infection, longer recovery times, and potential adhesions that may affect future pregnancies.
- Faster postpartum recovery: Women who deliver vaginally often experience less pain and can resume activities sooner than those who undergo major abdominal surgery.
- Lower neonatal morbidity in low-risk cases: Studies indicate that well-managed vaginal breech births can yield comparable outcomes to C-sections for babies under 3,800 grams with no additional risk factors.
- Empowerment and autonomy: Choosing a vaginal breech birth aligns with a woman’s right to informed consent and personalized care, moving away from paternalistic medical practices.
- Cost-effectiveness: Vaginal deliveries reduce healthcare costs associated with surgical interventions, including anesthesia, hospital stays, and postoperative care.
Comparative Analysis
| Vaginal Breech Birth | Cesarean Section for Breech |
|---|---|
|
|
Future Trends and Innovations
The future of breech position baby management lies in two intersecting trends: the resurgence of midwifery-led care and the integration of technology to assess fetal positioning and pelvic capacity. In countries like the Netherlands, where midwives attend nearly 30% of breech births, outcomes are comparable to those in high-intervention settings, suggesting that expertise—not just setting—determines success. Advances in 3D ultrasound and AI-driven fetal monitoring may soon enable earlier identification of optimal breech candidates, reducing the need for last-minute C-sections. Additionally, research into the "breech tilt" technique (a modification of the McRobert’s maneuver) shows promise in easing deliveries without increasing perinatal risks.Another frontier is the global variation in breech birth practices. While the U.S. and parts of Europe lean toward C-sections, countries with strong midwifery traditions continue to demonstrate that vaginal breech births can be safe when managed by skilled providers. As birth becomes more decentralized—with home births and birth centers gaining traction—the demand for breech-competent practitioners will rise. The challenge will be to standardize training without stifling the adaptability that defines physiological birth. Ultimately, the goal is to ensure that every woman, regardless of her baby’s position, has access to evidence-based options.
Conclusion
The story of breech position babies is one of progress and persistence. What was once a routine part of obstetrics became a cautionary tale, only to reemerge as a testament to the adaptability of both medicine and human physiology. The data is clear: not all breech births are created equal, and the one-size-fits-all approach to C-sections is giving way to a more nuanced understanding of risk and possibility. For parents facing a breech diagnosis, the message is simple: ask questions, seek providers with experience, and recognize that a vaginal birth is not only possible but sometimes the safest choice.The evolution of breech birth practices also reflects a larger cultural shift toward respecting the body’s capacity to birth in diverse ways. As research continues to unpack the myths surrounding breech position babies, the hope is that women will no longer feel forced into a binary choice but empowered to make decisions aligned with their values and circumstances. The future of breech birth isn’t just about medical innovation; it’s about reclaiming the trust that birth—in all its variations—is a natural, not a medicalized, process.
Comprehensive FAQs
Q: Is a vaginal breech birth safe for my baby?
A: Safety depends on multiple factors, including the type of breech (frank is generally safer than footling), the baby’s estimated weight, and the provider’s experience. Studies show that under 3,800 grams with an experienced midwife or obstetrician, vaginal breech birth can be as safe as a C-section. However, high-risk cases (e.g., preterm breech, malpresentation) may still require a C-section. Always discuss your specific risks with your healthcare provider.
Q: Can external cephalic version (ECV) turn a breech baby head-down?
A: ECV is a procedure performed around 37 weeks to manually turn a breech baby into a head-down position. Success rates vary (40–70%) and depend on the baby’s position, placenta location, and amniotic fluid volume. While effective, ECV carries a small risk of placental abruption or preterm labor, so it’s typically offered to low-risk pregnancies. If unsuccessful, a breech birth plan should be discussed.
Q: What are the signs that a vaginal breech birth may not be safe?
A: Red flags include prolonged labor, fetal distress (abnormal heart rate patterns), excessive bleeding, or signs of head entrapment (where the baby’s head fails to deliver after the body). Other high-risk factors are a baby over 3,800 grams, a transverse lie, or a history of preterm labor. Continuous monitoring by a breech-trained provider is essential to detect these signs early.
Q: How can I find a provider experienced in breech births?
A: Start by asking your current provider about their breech delivery volume. If their experience is limited, seek referrals to a hospital or birth center with a history of successful vaginal breech births. Organizations like the Birth Psychology network or local midwifery groups can also connect you with specialized practitioners. In some regions, breech-competent midwives attend home births, which may offer more flexibility.
Q: Are there specific exercises or positions to encourage a breech baby to turn?
A: While no exercise guarantees a breech baby will turn, certain practices may support optimal positioning. The "breech tilt" (lying on your hands and knees for 10–15 minutes daily) and pelvic tilts can encourage descent. Avoiding pressure on the lower back (e.g., sleeping on your left side) and staying active may also help. However, these methods are not substitutes for medical interventions like ECV or a breech birth plan.
Q: What’s the recovery like after a vaginal breech birth?
A: Recovery is generally similar to a head-down vaginal birth, though some women report more perineal stretching due to the baby’s position. Pain management may include ice packs, sitz baths, and mild analgesics. Most women can resume light activities within 2–6 weeks, though heavy lifting should be avoided for 4–6 weeks. Breastfeeding may be more challenging initially due to positioning, but lactation consultants can provide support.
Q: Can a breech baby be delivered safely at home?
A: Home breech births are possible but require a highly experienced midwife, a well-equipped birth space, and immediate transfer options if complications arise. Countries like the Netherlands report low intervention rates for planned home breech births, but this is not standard in the U.S. or many other regions. If considering a home birth, ensure your midwife has a high volume of breech deliveries and a clear emergency protocol.
Q: Does insurance cover breech birth planning or ECV?
A: Coverage varies by provider and country. In the U.S., most insurance plans cover ECV as a standard obstetric procedure, though out-of-pocket costs (e.g., ultrasound guidance) may apply. Vaginal breech birth planning is typically covered if medically indicated, but some insurers may require prior authorization. Always verify with your provider and insurance company to avoid unexpected expenses.
Q: What’s the success rate of vaginal breech births?
A: Success rates depend on the provider’s experience, breech type, and hospital protocols. In specialized settings, success rates range from 60–80% for frank breech presentations. Footling breech has lower success rates (30–50%) due to higher risks of cord prolapse. The 2000 Term Breech Trial found that planned home births with midwives had similar neonatal outcomes to hospital C-sections, but these results are not universally replicable.
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of versiliasolutions.oneagency.co.