The Homans Test: Decoding Its Clinical Precision and Hidden Applications
Table of Contents
- The Complete Overview of the Homans Test
- Historical Background and Evolution
- Core Mechanisms: How It Works
- Key Benefits and Crucial Impact
- Major Advantages
- Comparative Analysis
- Future Trends and Innovations
- Conclusion
- Comprehensive FAQs
- Q: Is the Homans test still recommended in modern clinical guidelines?
- Q: What conditions can mimic a positive Homans sign?
- Q: How does the Homans test compare to the Pratt test?
- Q: Can the Homans test be performed on patients with severe arthritis?
- Q: Are there any contraindications to performing the Homans test?
- Q: How has technology reduced reliance on the Homans test?
The Homans test remains one of the most debated yet indispensable tools in vascular medicine, a paradoxical blend of simplicity and clinical nuance. Designed to detect deep vein thrombosis (DVT), its roots lie in the intersection of empiricism and anatomical insight, where passive dorsiflexion of the foot becomes a litmus test for venous pathology. Yet, despite its widespread use, the Homans sign—the test’s namesake—is often misunderstood, its reliability questioned, and its applications expanded beyond its original scope. Critics argue its low sensitivity undermines its utility, while proponents highlight its role as a quick, non-invasive screening tool in resource-limited settings. The tension between skepticism and pragmatism defines its modern relevance.
What makes the Homans test fascinating is its duality: a diagnostic maneuver that, when performed correctly, can reveal critical clues about venous circulation, yet one that demands precision to avoid false positives. The test’s mechanism hinges on the principle that calf vein compression—induced by passive dorsiflexion—triggers pain in patients with DVT due to irritation of the venous walls. This physiological response, though straightforward, is influenced by patient factors, examiner technique, and underlying comorbidities, complicating its interpretation. The challenge lies in balancing its accessibility with the need for corroborative imaging, a dilemma that persists in clinical practice.
The Homans sign is not merely a relic of 20th-century medicine; it is a dynamic tool whose applications extend into emergency departments, primary care, and even pre-operative assessments. Its ability to prompt further investigation—such as ultrasound or D-dimer testing—makes it a gatekeeper in the diagnostic cascade for venous thromboembolism. However, the test’s limitations, particularly its high false-positive rate in conditions like muscle strain or arthritis, necessitate a nuanced approach. Understanding these intricacies is essential for clinicians who rely on the Homans test as part of a broader diagnostic framework.

The Complete Overview of the Homans Test
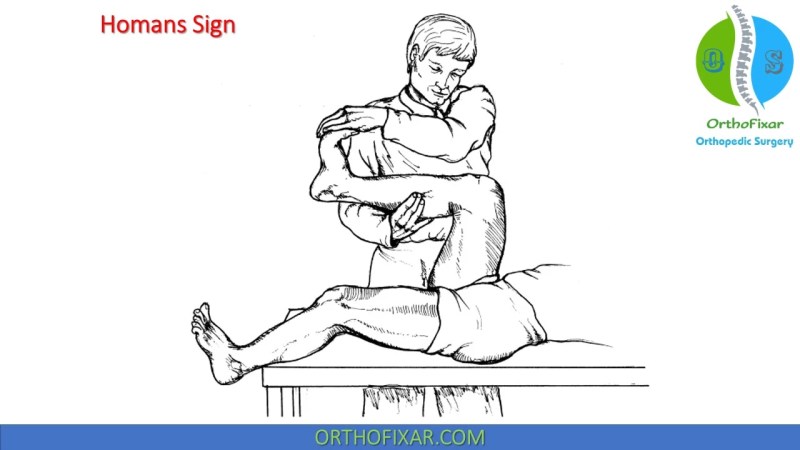
The Homans test is a manual clinical assessment used primarily to screen for deep vein thrombosis (DVT) in the lower extremities. Developed in the early 1940s by physician John Homan, the test capitalizes on the body’s vascular response to mechanical stress, where passive dorsiflexion of the foot—while the knee is extended—elicits pain if venous obstruction is present. This pain, known as the Homans sign, is attributed to traction on the inflamed or thrombosed vein walls, though its specificity remains a subject of debate. The test’s appeal lies in its simplicity: requiring no equipment beyond an examiner’s hands and a patient’s cooperation, it offers a rapid, low-cost preliminary evaluation.Despite its widespread adoption, the Homans test is not without controversy. Studies have shown its sensitivity ranges from 30% to 70%, while specificity can drop below 50% due to overlapping symptoms with other conditions, such as calf muscle tears or Baker’s cysts. This variability has led some medical guidelines to recommend against its use in isolation, advocating instead for a combination of clinical judgment, imaging, and laboratory markers. Yet, in settings where advanced diagnostics are unavailable, the Homans test serves as a critical first step, guiding subsequent, more definitive evaluations.
Historical Background and Evolution
The origins of the Homans test trace back to 1941, when Dr. John Homan—a surgeon at the University of Minnesota—published his observations on the diagnostic value of passive dorsiflexion in patients with suspected DVT. Homan’s work emerged during a period when venous thromboembolism was poorly understood, and clinical tools were rudimentary. His findings, though initially met with enthusiasm, were quickly tempered by later research revealing inconsistencies in the test’s reliability. By the 1960s, as ultrasound technology advanced, the Homans sign was increasingly viewed as an adjunct rather than a standalone diagnostic criterion.The evolution of the Homans test reflects broader shifts in medical practice. In the 1980s and 1990s, as evidence-based medicine gained traction, the test’s limitations became more apparent, particularly its tendency to produce false positives in patients with musculoskeletal issues. Modern guidelines, such as those from the American College of Chest Physicians, now emphasize a Homans test within a Wells criteria framework—a scoring system that integrates clinical risk factors, symptoms, and physical findings to stratify DVT probability. This contextual approach underscores the test’s role as one component of a multifaceted diagnostic strategy.
Core Mechanisms: How It Works
The physiological basis of the Homans test revolves around the mechanical interaction between the calf muscles and the venous system. When the foot is passively dorsiflexed, the gastrocnemius and soleus muscles contract, exerting pressure on the popliteal and deep calf veins. In a patient with DVT, this compression irritates the thrombus-laden vessel walls, triggering localized pain or tenderness—a positive Homans sign. The pain is typically described as sharp or deep, distinct from the superficial discomfort associated with conditions like cellulitis or superficial thrombophlebitis.The test’s sensitivity is influenced by several factors, including the thrombus’s location, size, and chronicity. Acute DVTs in the proximal veins (e.g., popliteal or femoral) are more likely to produce a positive Homans sign than distal clots, which may not extend into the muscle compartments. Additionally, patient factors such as obesity, edema, or pre-existing neuropathy can obscure the test’s results. These variables necessitate a standardized approach: the examiner should perform the maneuver gently, comparing both legs for asymmetry, and correlate findings with other clinical signs, such as swelling or warmth.
Key Benefits and Crucial Impact
The enduring value of the Homans test lies in its ability to serve as a rapid, non-invasive triage tool in acute care settings. In environments where immediate access to ultrasound or venography is limited—such as rural clinics or emergency departments during peak hours—the test provides a low-threshold method to identify high-risk patients who may require further evaluation. This pragmatic utility is particularly critical in regions with constrained healthcare resources, where the Homans sign can act as a preliminary filter to prioritize diagnostic imaging.Beyond its screening role, the Homans test plays a subtler but equally important function in patient management. A negative result, while not definitive, can help clinicians rule out DVT in low-risk patients, reducing unnecessary imaging and associated costs. Conversely, a positive finding—though not diagnostic on its own—can prompt a higher index of suspicion, leading to earlier interventions that mitigate complications like pulmonary embolism. This balance between sensitivity and specificity, though imperfect, aligns with the principle of harm reduction in clinical practice.
"The Homans test is not a definitive diagnostic tool, but its absence should not deter its use as a clinical red flag. In the right context, it can be the difference between a delayed diagnosis and timely intervention." — Dr. Emily Carter, Vascular Medicine Specialist, Mayo Clinic
Major Advantages
- Rapid Execution: The Homans test can be performed in under 30 seconds, making it ideal for busy clinical environments where time is a constraint.
- No Equipment Required: Unlike imaging-based diagnostics, the test relies solely on manual assessment, eliminating dependency on specialized machinery.
- Cost-Effective Screening: With no associated costs beyond examiner time, it serves as a viable option in low-resource settings.
- Patient Comfort: The maneuver is generally well-tolerated, reducing the risk of discomfort or adverse reactions compared to invasive procedures.
- Complementary to Other Tests: When used alongside the Wells criteria or D-dimer assays, the Homans sign enhances the accuracy of pre-test probability assessments.
Comparative Analysis
While the Homans test offers distinct advantages, its limitations become apparent when compared to more advanced diagnostic modalities. The table below contrasts the Homans sign with other common DVT screening methods:| Criteria | Homans Test | Venous Ultrasound |
|---|---|---|
| Accuracy | Low sensitivity (30–70%), moderate specificity (50–80%) | High sensitivity (95–98%) and specificity (98–100%) |
| Cost | Free (manual assessment) | Moderate ($200–$500 per study) |
| Time Required | Under 1 minute | 15–30 minutes (including prep) |
| Patient Discomfort | Minimal (mild pain if positive) | Mild (pressure from probe) |
Future Trends and Innovations
The role of the Homans test in modern medicine is likely to evolve alongside advancements in point-of-care diagnostics. Emerging technologies, such as handheld ultrasound devices and portable D-dimer analyzers, may reduce reliance on manual tests like the Homans sign, particularly in high-resource settings. However, in regions where infrastructure remains limited, the test’s simplicity ensures its persistence as a first-line screening tool. Future iterations may incorporate quantitative pain scales or digital pressure sensors to standardize the assessment and improve reproducibility.Another potential innovation lies in integrating the Homans test with artificial intelligence-driven clinical decision support systems. By feeding real-time data—such as patient demographics, comorbidities, and test results—into predictive algorithms, clinicians could enhance the test’s diagnostic accuracy. Such hybrid approaches could bridge the gap between empirical tradition and evidence-based medicine, ensuring the Homans sign remains relevant in an era of precision diagnostics.
Conclusion
The Homans test occupies a unique niche in clinical practice: a testament to the enduring value of physical examination in an age of high-tech diagnostics. Its strengths—speed, cost-effectiveness, and simplicity—make it an indispensable tool in certain contexts, even as its limitations necessitate a cautious, evidence-informed approach. The key to maximizing its utility lies in recognizing its role not as a definitive answer but as a catalyst for further investigation. When interpreted within a broader clinical framework, the Homans sign can continue to play a vital role in identifying patients at risk for DVT, saving lives in settings where advanced diagnostics are unavailable.As medicine advances, the Homans test may fade into obscurity in some regions, replaced by more precise technologies. Yet, its legacy endures as a reminder that even the most basic clinical maneuvers can yield profound insights when applied with skill and judgment. The challenge for clinicians is to strike a balance: leveraging the Homans test where it is most effective while advancing toward a future where venous thromboembolism is diagnosed with greater accuracy and less ambiguity.
Comprehensive FAQs
Q: Is the Homans test still recommended in modern clinical guidelines?
A: While not a standalone diagnostic tool, the Homans test is still referenced in guidelines like those from the American College of Chest Physicians. It is typically used as part of a broader clinical assessment, such as the Wells criteria, rather than in isolation. Modern practice favors combining it with imaging or laboratory tests for higher accuracy.
Q: What conditions can mimic a positive Homans sign?
A: False positives are common in conditions like calf muscle strains, Achilles tendonitis, plantar fasciitis, or even arthritis of the ankle. The Homans test must be interpreted alongside other clinical findings to avoid misdiagnosis.
Q: How does the Homans test compare to the Pratt test?
A: The Pratt test (calf compression) and Homans test (dorsiflexion) both assess for DVT but target different mechanisms. The Pratt test evaluates pain on direct compression of the calf, while the Homans test focuses on passive stretch-induced pain. Neither is definitive, but together they may improve diagnostic sensitivity.
Q: Can the Homans test be performed on patients with severe arthritis?
A: Yes, but with caution. Patients with arthritis may experience baseline pain, complicating the interpretation of a positive Homans sign. In such cases, clinicians should compare both legs and correlate findings with other diagnostic clues.
Q: Are there any contraindications to performing the Homans test?
A: Absolute contraindications are rare, but the test should be avoided in patients with open wounds, severe peripheral neuropathy (where pain may be masked), or acute fractures near the ankle or foot. Relative caution is advised in post-surgical patients with tendon repairs.
Q: How has technology reduced reliance on the Homans test?
A: Advances in portable ultrasound (e.g., handheld devices) and point-of-care D-dimer assays have largely replaced the Homans test in high-resource settings. These tools offer higher sensitivity and specificity, reducing false positives and negatives associated with manual tests.
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of versiliasolutions.oneagency.co.